
What is Prostate Artery Embolization?
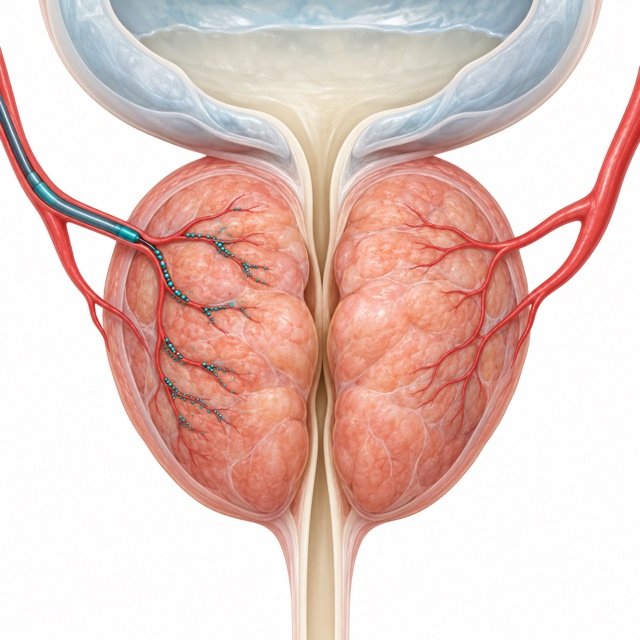
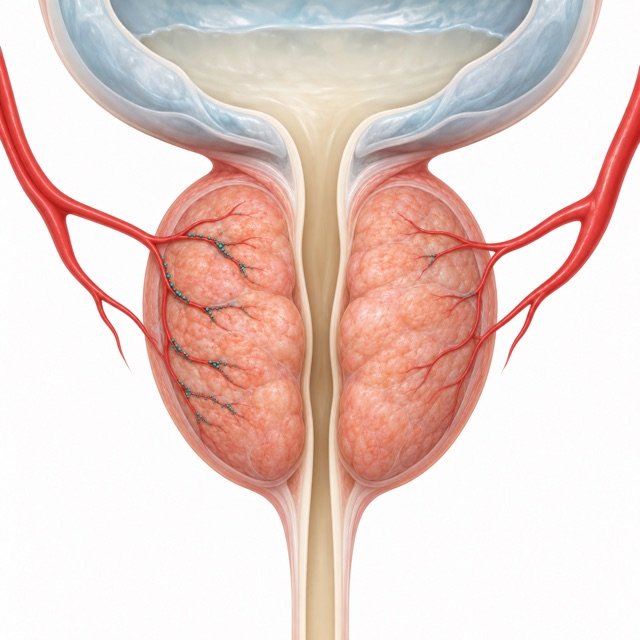
PAE treats an enlarged prostate by working from inside the blood vessels. Through a pinpoint access in the groin, our interventional radiologist guides a thin intra-arterial catheter — under live X-ray imaging — to the small arteries that feed the prostate. There, microscopic particles (the “medicine”) are released to reduce the gland's blood supply. Deprived of that supply, the enlarged tissue softens and shrinks over the following weeks, relieving pressure on the urethra and restoring flow.
Then the catheter is removed. No cutting of the prostate. Nothing passed through the urethra. No urinary catheter to go home with. No implant left in your body. The access point in the groin is closed the same day, and most men are back to their routine within one to three days.
Why men choose PAE
Every other effective BPH procedure works through the urethra — and most either remove tissue, heat it, or leave an implant behind. PAE is the exception. It preserves sexual function, avoids the irritative healing phase of transurethral treatments, and treats prostates of virtually any size, including very large glands (well over 80–100 g) that disqualify men from Rezūm or UroLift.
PAE is also the standout option for men who can't have surgery — those on blood thinners, with cardiac or anesthesia risk, or who are catheter-dependent from urinary retention and want a path off the catheter.
The procedure, step by step
Before: a consultation with Dr. David Shusterman confirms BPH is the cause of your symptoms (and rules out anything else), with imaging to map your prostatic arteries.
The day of: you arrive at our outpatient center; no general anesthesia is needed. Dr. Yosef Golowa, our interventional radiologist, numbs a small spot in the groin and advances the catheter through the arterial system to each prostatic artery, embolizing both sides where anatomy allows. The procedure typically takes one to a few hours depending on anatomy. The catheter is withdrawn, the entry point is sealed, and after a short observation period you go home the same day.
After: some men notice mild pelvic discomfort, low-grade fever, or urinary frequency for a few days — “post-PAE syndrome,” a normal sign the treatment is working — managed with over-the-counter medication. We do not place a urinary catheter after PAE. The only men who go home with one are men who arrived with one: if you came to us already in retention, your existing catheter stays briefly to give the bladder time to recover, then we remove it. Your follow-up happens with our urology team, in the same office — flow improves progressively as the gland shrinks over weeks to about three months.
No one in New York City has done more PAEs
Prostatic arteries are small, variable, and often share origins with vessels you must not embolize. PAE is one of the most technically demanding procedures in interventional radiology, and published outcomes track closely with operator experience. We have performed over 1,000 PAE procedures — more than any other center in New York City — with minimal to no recorded side effects, including very large prostates and complex anatomy referred to us from elsewhere.
Behind that number is a structure that is likely unique in New York: urology and interventional radiology in one office. Dr. David Shusterman evaluates you thoroughly as a urologist and confirms PAE is the right answer. Dr. Yosef Golowa performs the embolization. Then you return to the urology team — the physicians most capable of managing your prostate health going forward — for all follow-up. At a hospital, those are three departments and three sets of records. Here, it's one hallway.
PAE vs. UroLift and TURP: recovery and everyday life
Why patients choose PAE
PAE offers an outpatient approach with a shorter recovery than TURP, usually without a urinary catheter. It treats the prostate through an artery rather than passing an instrument through the urethra.
How each treatment works
Three different approaches to opening the urinary channel.
PAE
Tiny particles reduce blood flow to the prostate, helping it shrink over time. Treatment reaches the gland through an artery.
UroLift
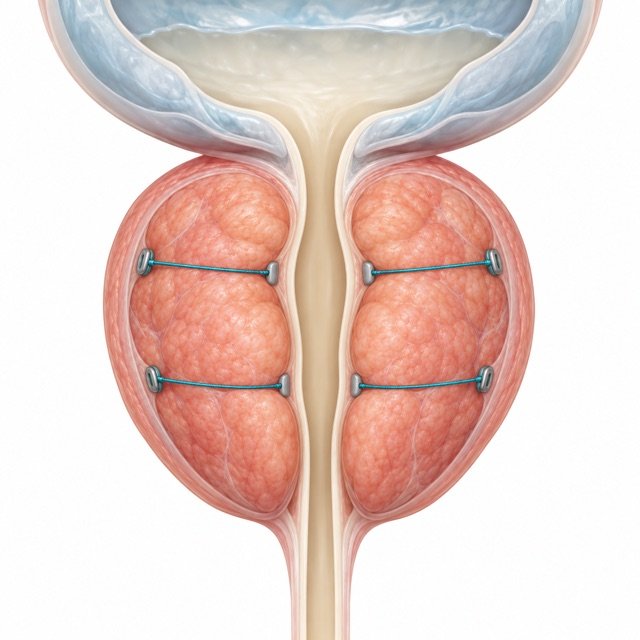
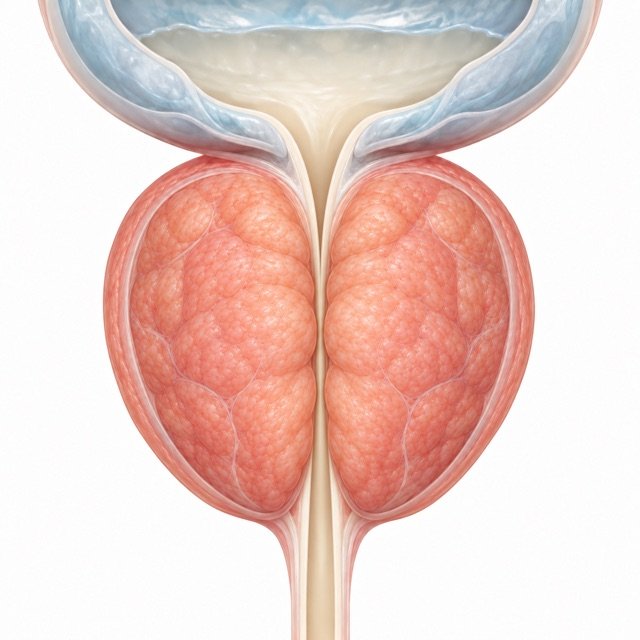
Small permanent implants hold prostate tissue away from the urinary channel. The delivery device passes through the urethra.
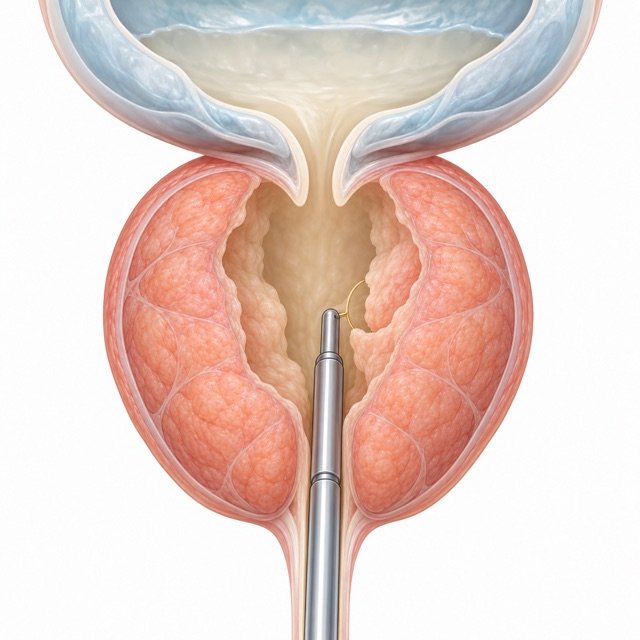
TURP
An instrument passed through the urethra removes inner prostate tissue to create a wider channel.
Simplified animations show treatment mechanisms. Time is condensed: prostate shrinkage after PAE develops over following weeks. Anatomy, treatment details and results vary.
| What matters to you | PAE | UroLift | TURP |
|---|---|---|---|
| Recovery | Usually a shorter recovery than TURP; your care team will advise when to resume work and exercise. | Normal activities often resume within a few days; recovery varies. | Usual activities often resume in 2–4 weeks; full healing may take up to 6 weeks. |
| Pain and discomfort | Local numbing and light sedation; temporary pelvic discomfort, burning or urinary frequency can occur. | Temporary burning, pelvic discomfort, urgency or blood in the urine can occur. | Soreness, bladder irritation and bleeding may occur during healing; pain relief is provided. |
| Urinary catheter after treatment | Usually not needed. Existing retention or difficulty urinating afterward may require one. | Most patients do not need one; a short-term catheter may be required. | Usually required temporarily after surgery. |
| Hospital stay | Usually home the same day; an overnight stay is not routinely needed. | Usually a same-day outpatient procedure. | Often requires a hospital stay; discharge timing depends on recovery and local practice. |
| Through the urethra | No — accessed through an artery in the wrist or groin. | Yes — implants are placed through the urethra. | Yes — obstructing tissue is removed through the urethra. |
| What remains in the prostate | Microscopic embolic particles; no UroLift implant. | Permanent implants hold prostate tissue apart. | No permanent implant; prostate tissue is removed. |
UroLift also offers outpatient treatment and a quick return to activities. PAE’s distinct advantage is the arterial approach, without urethral instrumentation or permanent UroLift implants. No procedure is guaranteed to be painless or catheter-free.
Recovery time is different from symptom improvement: after PAE, urinary relief develops as the prostate shrinks over the following weeks. Your prostate anatomy, bladder function and goals determine which treatment fits.
PAE uses a temporary catheter inside an artery during the procedure. The comparison above concerns a urinary catheter left in the bladder afterward.